What an Anion Gap Shows
The anion gap is a derived value used in lab medicine to assess the difference between routinely measured cations and anions in electrolytes. In simple terms, it helps clinicians and laboratory staff think about the balance of charged particles in blood and whether there are extra unmeasured anions present. This makes it a useful marker of electrolyte balance and broader acid-base status.
An Anion Gap Calculator is a simple diagnostic aid that translates common lab values into an interpretable number. The result does not diagnose a disorder by itself, but it adds important context to a patient’s serum chemistry and overall electrochemical balance. Because the anion gap reflects the relationship between positive and negative ions, it can reveal an underlying metabolic disturbance even when the rest of the panel seems only mildly abnormal.
From a physiology perspective, the anion gap is a window into buffer systems and acid accumulation. When acids accumulate, their anions may not be directly measured in a standard electrolyte panel. That is why the anion gap acts as a kind of anion difference—a screening measure that can point toward hidden biochemical changes.
In laboratory medicine, the value is best understood as part of a broader clinical interpretation. It complements, rather than replaces, history, exam findings, and other tests. Used correctly, it can help narrow a differential diagnosis and guide follow-up testing.
Anion Gap Formula & Calculation Inputs
The main calculation formula is simple. Most commonly, the anion gap is calculated from sodium, chloride, and bicarbonate:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some testing labs report a slightly different version if potassium is included, but the sodium-based formula is the most common in routine practice. An Anion Gap Calculator directly applies this formula and returns a value that can be compared with the local interpretive range.
The necessary inputs come from the serum chemistry or chemistry analyzer output:
- Sodium: the major measured extracellular cation. Chloride: the principal anion measured. Bicarbonate: usually reported as total CO2 on the chemistry panel, used as a bicarbonate proxy in many settings.
Since the result depends completely on these three values, the quality of the output depends on the quality of the input. A small error in any one test can shift the final number enough that it changes clinical interpretation. This is why understanding the underlying measurement method is important in laboratory medicine.
A lot of users think of the result as a single number, but it is more helpful to view it as a reflection of the underlying serum chemistry and the patient’s current acid-base status. When the calculator output is unexpected, it is worth reviewing the original analytes before drawing conclusions.
How to Interpret a Typical, Raised, or Decreased Anion Gap
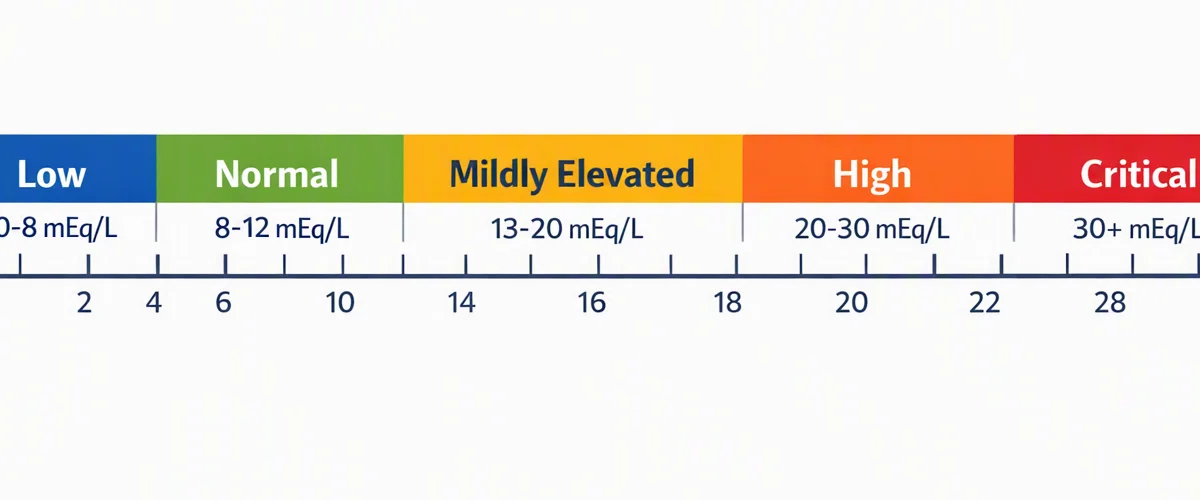
Interpretation begins with the local reference range. Multiple laboratories may use distinct analyzers, calibration approaches, and reporting conventions, so there is no universal “normal” value that applies everywhere. The same numeric result may be interpreted another way depending on the platform and the institution’s reference range.
A within-range anion gap suggests that the measured electrolytes are in proper proportion and that there is no obvious increase in unmeasured anions. However, a normal value does not eliminate disease. Some forms of metabolic acidosis occur with a normal anion gap, especially when bicarbonate loss is matched by chloride gain.
A high anion gap suggests that extra acids or negatively charged substances are present in the blood. This pattern is classically associated with high anion gap metabolic acidosis, where the extra acid is reflected in the increased gap. In contrast, a normal value in the setting of acidosis can point toward normal anion gap metabolic acidosis, which has a different set of etiologies and follow-up steps.
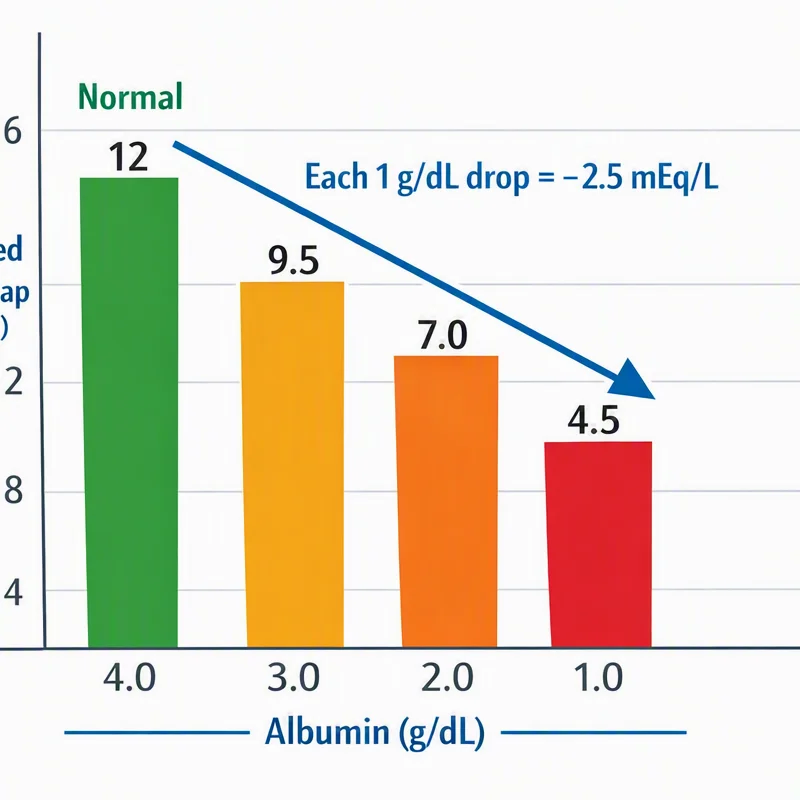
Albumin is one of the main modifiers of interpretation. Because albumin is a negatively charged protein, lower levels can reduce the apparent gap and mask clinically important acid-base changes. That means interpretation should always consider whether the measured number fits the patient’s broader clinical chemistry picture.
In practice, the result is best interpreted as part of the overall acid-base disorders assessment, not as a stand-alone answer. The same number can mean varied things depending on whether the patient has symptoms, abnormal lactate, renal dysfunction, or other lab abnormalities.
Albumin Correction and Why It’s Important
Hypoalbuminemia is a major reason the measured anion gap can underestimate the true burden of hidden acids. Since serum albumin carries a negative charge, a decreased albumin concentration diminishes the expected gap even when other acids are present. This is why many laboratory clinicians use a corrected anion gap.
The corrected result adjusts the observed value upward when albumin is low, making the estimate more practically useful. In many workflows, albumin correction helps uncover a hidden metabolic acidosis that might otherwise appear minimal or even absent. The goal is not to force every result into a single interpretation, but to improve the accuracy of the corrected result when protein abnormalities are present.
Key reasons it matters:
- It increases detection of acid-base abnormalities when serum albumin is low. It helps avoid underestimating high anion gap metabolic acidosis. It promotes better clinical interpretation in severely ill or hospitalized patients.
A calculator that includes albumin correction can be especially helpful because it turns a raw number into a more meaningful estimate of acid-base burden. In other words, the adjusted value can better reflect the patient’s actual electrolyte balance and the likely presence of unmeasured anions.
For laboratory medicine, the key point is that a single uncorrected number may be incomplete. When albumin is low, the Anion Gap Calculator should be used as a screening tool plus a first step for further assessment rather than the final word.
Frequent Causes of an Elevated Anion Gap
An high result often suggests acid accumulation from added organic or inorganic acids. The classic teaching is high anion gap metabolic acidosis, but test interpretation should emphasize the root cause rather than the pattern alone.
3 of the most common causes are lactic acidosis, ketoacidosis, and renal failure.
- Lactic acidosis: Increased lactate production or impaired clearance can increase the gap as lactate-associated anions accumulate. Ketoacidosis: Ketone bodies contribute unmeasured anions, often resulting in a clearly elevated gap. Renal failure: Reduced excretion of acid byproducts can lead to retention of unmeasured anions and a progressively higher gap.
Additional factors may also be present, but these three diagnoses are common anchor points in the differential diagnosis. In the laboratory context, the anion gap helps decide whether a patient’s metabolic disturbance is likely due to hidden acid retention or to another mechanism.
It is useful to remember that an elevated gap is not itself a diagnosis. Instead, it is a clue that prompts additional testing, such as lactate, ketones, renal function markers, or toxicology studies when appropriate. The value becomes most useful when paired with other lab values and the clinical picture.
Reasons of a Decreased Anion Gap
A decreased result is not as common than a raised one, but it can still be diagnostically important. The leading explanation is hypoalbuminemia, because a decreased albumin level lowers https://anion-gap-tool964.fotosdefrases.com/how-methanol-poisoning-affects-the-anion-gap the expected number. If albumin is not considered, the result may look falsely reassuring or simply “off” without a clear cause.
Paraproteinemia is another important cause. Certain abnormal proteins can alter the charge balance in blood and reduce the measured gap. In some patients, this finding may be an early clue that further evaluation of protein abnormalities is needed.
Laboratory error must also be considered. A low value may reflect a specimen issue, analyzer issue, or transcription problem rather than true physiology. That is why repeating the panel and reviewing the original serum chemistry is often the first practical step.
Other reasons can include interference with the measurement method or unusual shifts in electrolytes, but the three major causes above should be checked first. When the result is unexpectedly low, the best practice is to check the numbers, review the patient’s albumin, and reassess whether the result matches the broader biochemical context.
Although clinicians often focus on elevated values, a low gap can reveal important pathology or analytical issues. In laboratory medicine, that makes it just as important to the overall interpretation process.
Clinical Use Cases in Clinical Laboratory Practice
The anion gap has a well-defined role in evaluating acid-base disorders. In day-to-day laboratory medicine, it is commonly used alongside the arterial blood gas and the serum chemistry panel to aid in identifying whether a patient has an acid-base problem and what form it may be.
Typical use cases include:
- Recognizing a possible hidden metabolic problem when bicarbonate is low. Assisting in classifying metabolic acidosis as high gap or normal gap. Supporting the evaluation of unexplained electrolyte abnormalities. Serving as a quick screening tool before more specialized testing.
In a workflow setting, the calculator can bridge serum chemistry results with the broader acid-base picture. For instance, a low bicarbonate on the chemistry panel plus an increased gap suggests acid retention rather than simple bicarbonate loss. That distinction is important because it changes the next diagnostic step.
The result also assists with clinical interpretation when the arterial blood gas and chemistry panel do not seem to match perfectly. This can happen because of timing differences, sample handling, or different measurement platforms. The anion gap helps bridge those data points and provides a practical way to interpret the patient’s acid-base status.
When used appropriately, the calculator is more than arithmetic. It is a structured way to turn routine lab data into a more informative assessment of metabolic health.
Constraints, Problems, and Recommended Practices
While the anion gap is valuable, it has significant limitations. The key issue is that the result depends on how the lab measures electrolytes. Contemporary analyzers often use ion-selective electrodes, and various platforms can yield different numeric results. This means the same patient may have a different reported gap from one system to another.
Measurement error can also distort the answer. Minor inaccuracies in sodium, chloride, or bicarbonate can shift the gap enough to change interpretation, especially when the result is near the reference range. Preanalytical issues, sample contamination, and analyzer interference should all be considered when the number seems inconsistent with the clinical picture.
The delta gap is another important concept in difficult cases. It compares the change in the anion gap with the change in bicarbonate, helping to identify mixed acid-base disorders. In other words, it can show whether several process is affecting the patient at the same time. This is especially valuable when the raw number alone does not explain the overall pattern.
Good practice for using the calculator include:
- Confirm the inputs are from the same sample and the same time point when possible. Check the local reference range rather than assuming a universal normal value. Check serum albumin before final interpretation. Consider ion-selective electrodes and platform differences when comparing results. Consider using the delta gap when mixed disorders are suspected.
Most importantly, the anion gap should be interpreted as part of the overall acid-base disorders assessment. It is a strong clue, not a standalone diagnosis. When used with the rest of the electrolyte panel and the clinical context, it becomes a practical tool for laboratory medicine.
Frequently Asked Questions on the Anion Gap Calculator
What exactly is an Anion Gap Calculator used for?
An anion gap calculator is used to rapidly estimate the gap between reported cations and anions from routine lab values. It helps with interpretation of electrolyte data, assists assessment of metabolic acidosis, and can suggest the presence of unmeasured anions. In laboratory medicine, it serves as a useful diagnostic aid rather than a final diagnosis.
How can you calculate the anion gap from lab values?
The usual calculation formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). Many calculators use values from a standard electrolyte panel or serum chemistry report. The result should then be compared with the lab’s reference range for correct interpretation.
When should the anion gap be corrected for albumin?
Use albumin correction when serum albumin is low, especially in hypoalbuminemia. Low albumin can make the measured gap look falsely normal or low, so a corrected anion gap can provide a better assessment of the patient’s acid-base state. This is particularly useful when evaluating suspected metabolic acidosis.
What might a high anion gap indicate?
A high value usually suggests high anion gap metabolic acidosis, meaning extra acids or other unmeasured anions are present. Common causes include lactic acidosis, ketoacidosis, and renal failure. The result should be interpreted alongside the rest of the lab data and clinical findings to narrow the differential diagnosis.
May a low anion gap be clinically significant?
Yes. A low result can point to hypoalbuminemia, paraproteinemia, or laboratory error. It may also reflect analytical or preanalytical issues affecting the measurement method. Even if less dramatic than a high value, a low result can still be an meaningful clue in laboratory medicine and should not be ignored.