What the Anion Gap Shows
The anion gap is a practical way to measure acid-base balance by reviewing the main cationic and negatively charged components found in serum electrolytes. It enables clinicians identify hidden alterations in the body’s chemistry that may not be obvious from a basic electrolyte review alone.
At its core, the anion gap reflects the difference between routinely measured cations and anions in a electrolyte panel. Because not every charged particle is directly measured, the result gives an indirect estimate of unmeasured anions. This makes it a valuable marker in the diagnostic evaluation of an acid-base disorder, especially when metabolic acidosis is suspected.
An elevated or reduced gap does not diagnose a condition by itself. Instead, it serves as a clue that can guide laboratory interpretation, prompt further testing, and support a broader review of serum chemistry and clinical findings. In practice, an anion gap calculator is a calculation tool that helps organize these measured values efficiently and consistently.
How the Anion Gap Calculator Functions
A anion gap calculator uses the key measured electrolytes from blood testing to estimate the difference between positively charged ions and anions. The standard inputs are sodium, chloride, and bicarbonate. These results are generally included in routine serum chemistry results.
The usual form of the calculation matches sodium concentration with chloride concentration and bicarbonate level. As sodium is the dominant measured cation and chloride and bicarbonate are key measured anions, the formula can show shifts in electrolyte imbalance that may indicate a metabolic problem.
This calculation is especially helpful in clinical decision support because it gives a fast snapshot of anion gap interpretation. A clinician might use it to see whether a patient’s symptoms and lab values fit a metabolic disturbance such as acidosis, whether the pattern suggests extra unmeasured anions, or whether the result is likely within the lab reference range.
In many cases, the calculator is used directly with the numbers from the lab report. That provides a practical method to interpret measured values without repeating the same equation each time.
Assessed Serum Electrolytes Required to Calculate the Result
To determine the anion gap accurately, you need the appropriate serum electrolytes from the same blood draw if possible. The usual inputs are serum sodium, serum chloride, and serum bicarbonate. These values come from the electrolyte panel and are key for reliable laboratory interpretation.
Consistency matters because the calculation assumes the numbers https://rentry.co/qzdytvyg reflect the same exact physiologic moment. If one result is outdated, drawn from a different sample, or affected by a testing issue, the gap may not accurately represent the patient’s current acid-base balance.
Along with the core values, clinicians often review related findings from the broader electrolyte panel. For example, an abnormal bicarbonate level may suggest buffering changes, while a shifted chloride concentration may help indicate whether the pattern looks like a normal anion gap issue or a high anion gap process.
Because the result depends on measured electrolytes, even small changes can affect the final number. This is why careful review of the source lab values is an important step before drawing conclusions.
Step-by-Step Anion Gap Formula
The usual anion gap formula is straightforward:
Na minus Cl minus HCO3
Here, Na represents sodium, Cl stands for chloride, and HCO3 stands for bicarbonate. Certain versions of the formula also add potassium, but the most widely used approach in routine practice is the one above. It is preferred because it is simple, fast, and practical for everyday anion gap interpretation.
To work with the formula, start with the sodium concentration, then take away the chloride concentration, and take away the bicarbonate level. The result is the anion gap. An Anion Gap Calculator performs this automatically, reducing the chance of arithmetic mistakes and supporting efficient review of measured values.
The resulting number is then compared with the normal range or reference range provided by the laboratory. Different laboratories may use slightly different cutoffs depending on methodology and reporting standards, so it is best to interpret the result in the context of the specific lab reference range attached to the report.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the formula gives an anion gap of 14. Whether that is considered normal depends on the lab’s established reference range and the overall clinical picture.
Normal, Increased, and Reduced Anion Gap Findings
A result within the expected reference range is often described as a within-range anion gap. That does not automatically mean everything is normal, but it suggests there is no obvious elevation in unmeasured anions based on the available values.
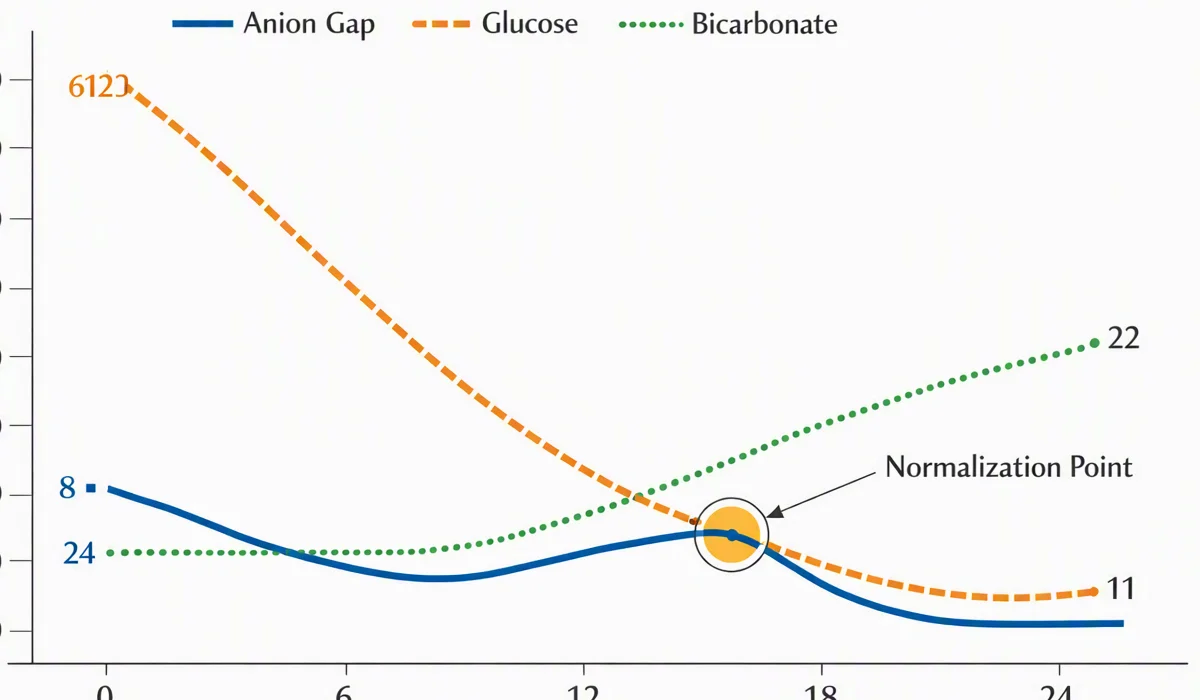
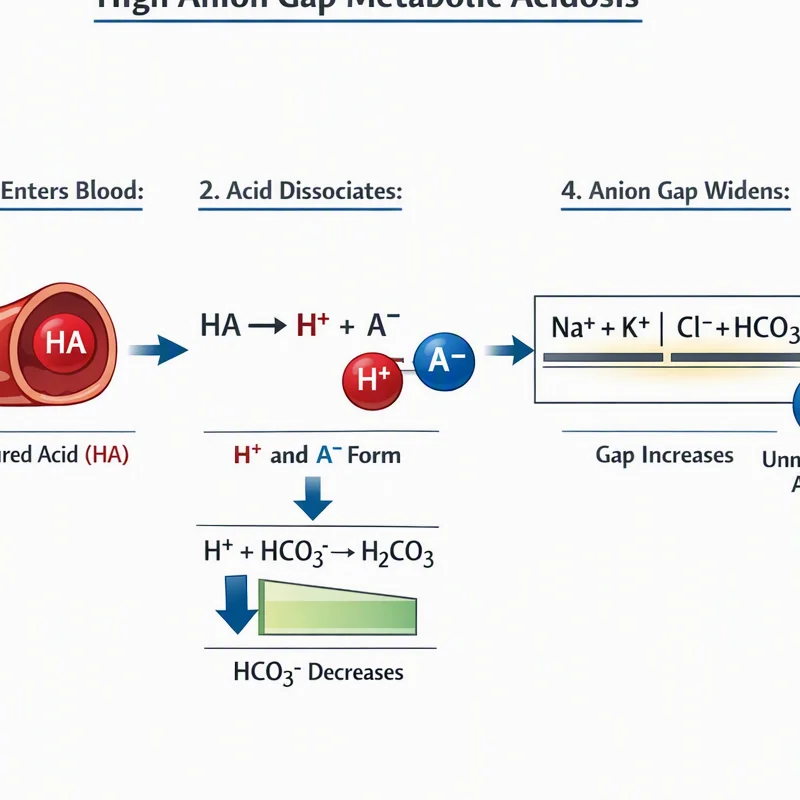
A elevated anion gap suggests an excess of unmeasured acids or anions. This pattern is commonly associated with metabolic acidosis and often prompts a more comprehensive evaluation for underlying reasons. In this setting, the anion gap becomes a central part of anion gap interpretation and helps refine the differential diagnosis.
A decreased anion gap is uncommon but can still be clinically relevant. It may reflect changes in protein levels, analytical issues, or shifts in measured electrolytes. Because low values can be missed, careful review is important before assuming the result is irrelevant.
Assessing these categories requires attention to the lab reference range. A value that seems abnormal in one setting may be normal in another if the laboratory uses a different method or cutoff. That is why the reported reference range should consistently be checked before describing the result.
In the end, the result is not interpreted in isolation. It should be paired with symptoms, the overall electrolyte panel, and the broader clinical question that led to the test.
Frequent Causes of an Unexpected Anion Gap
An unexpected result often points toward a clear metabolic disorder. One of the main causes of a high anion gap is metabolic acidosis, where acids accumulate or buffering is reduced. Frequent examples include lactic acidosis, ketoacidosis, and renal failure.
Lactic acidosis can arise when tissues are underperfused, oxygen delivery is limited, or metabolism is generally stressed. In these situations, lactic acid increases, and the anion gap may increase because of added unmeasured acids.
Ketoacidosis is one more classic cause of high anion gap findings. When the body produces excess ketones, these acids raise the gap and may be seen with diabetes, starvation, or other states of reduced carbohydrate availability.
Renal failure can also increase the gap because the kidneys are less able to clear acid loads effectively. As acids collect, the result may shift away from the normal anion gap and toward a high-gap pattern.
On the other end, a low anion gap may appear when albumin is reduced, when there is a testing artifact, or when unusual ions affect the calculation. Because the pattern is uncommon, it should be reviewed closely with the rest of the serum electrolytes and the patient’s overall presentation.
Modifying the Anion Gap for Albumin
Albumin is a major unmeasured anion in blood, so it has a significant effect on the calculated gap. When hypoalbuminemia is present, the measured result may appear lower than expected even if extra acids are present. That is why albumin correction is an key part of modern anion gap interpretation.
The corrected anion gap refines the result to account for low albumin. This matters because a patient with hypoalbuminemia may have a misleadingly normal or only mildly elevated gap despite a significant acid-base problem. Without correction, the underlying disorder could be underestimated.
Using the corrected anion gap helps increase diagnostic accuracy, especially in patients with chronic illness, poor nutrition, inflammation, or other conditions associated with low protein levels. In these cases, the calculator should be used as part of a larger review rather than as a stand-alone number.
Albumin correction is not always required, but it is often useful when the measured result and the clinical picture do not match. When the gap seems unexpectedly low or borderline, checking the albumin level can aid interpretation and uncover hidden metabolic changes.
How to Interpret Results in Clinical Context
The best way to interpret an anion gap calculator is in combination with the overall clinical picture. A single value can point to a direction, but an definitive diagnosis depends on symptoms, medical history, and other labs. In practice, interpretation often includes the arterial blood gas, the electrolyte panel, and other markers of organ function.
The arterial blood gas can show whether the patient has acidemia or alkalemia and whether respiratory compensation is occurring. When combined with the electrolyte panel, it helps define the specific acid-base disorder. This is especially important if the bicarbonate is low or if the patient has signs of shock, dehydration, toxin exposure, or kidney dysfunction.
A high anion gap with low bicarbonate often suggests the presence of metabolic acidosis. But not all metabolic acidosis is the same. Some cases are related to lactic acid, some to ketones, and others to impaired renal clearance. The pattern of serum electrolytes can help identify which mechanism is most probable.
A normal value does not always exclude disease. For example, mixed disorders can mask abnormalities, and a low albumin level can blunt the expected rise. That is why anion gap interpretation should be paired with clinical examination, diagnosis-focused testing, and careful review of all available measured values.
Limitations and Common Calculation Errors
Even though the anion gap is easy to calculate, several issues can affect calculation accuracy. One of the most common is measurement error. If the source lab result is wrong, contaminated, or collected improperly, the final number may not reflect the patient’s true status.
Lab variation is another important factor. Different instruments and reporting methods can produce slightly different values for sodium, chloride, or bicarbonate. As a result, the same patient may have a different result depending on the laboratory, making the lab reference range essential for interpretation.
Another frequent problem is using mismatched results. If sodium was drawn at one time and chloride or bicarbonate at another, the value may be misleading. The preferred method is to use a single, consistent electrolyte panel whenever possible.
Readers should also avoid reading too much into a borderline abnormal result without clinical context. A small shift may be due to routine variation rather than a true metabolic disturbance. Likewise, a clearly abnormal value should prompt review of the entire clinical situation rather than a reflex conclusion based on the calculator alone.
In summary, the tool is only as good as the input. Careful review of serum electrolytes, attention to measurement error, and awareness of lab variation are key to dependable anion gap interpretation.
Frequently Asked Questions
What is a normal anion gap?
The anion gap normal range depends on the laboratory method and the reported reference range. In many settings, the value is considered normal when it falls within the lab’s stated cutoff. Because methods vary, the most accurate interpretation is the one that matches the specific lab reference range listed with the result.
How do you calculate the anion gap from measured electrolytes?
Use the standard anion gap formula: Na minus Cl minus HCO3. Enter the measured sodium, chloride, and bicarbonate values from the same electrolyte panel. An anion gap calculator makes this process faster and reduces the chance of arithmetic mistakes.
Why is albumin used to correct the anion gap?
Albumin is a major unmeasured anion, so low levels can make the gap appear falsely low. Albumin correction helps produce a more accurate corrected anion gap, especially in patients with hypoalbuminemia. This improves the detection of hidden acid-base abnormalities.
Why does there be a high anion gap?
Typical high-gap causes include lactate acidosis, ketosis-related acidosis, and renal failure. Such conditions elevate unmeasured acids or decrease acid clearance, causing acid-base acidosis and a greater calculated gap.
Can a low anion gap be clinically significant?
Absolutely. A reduced anion gap can be clinically significant, especially when linked to hypoalbuminemia, a testing issue, or other abnormalities in serum electrolytes. It should not be ignored, particularly if the result does not fit the rest of the acid-base equilibrium picture.